
For nighttime scenarios such as bedrooms, hotel guest rooms, elderly care spaces, and hospital wards, nighttime lighting must simultaneously address safety, comfort, and circadian health.
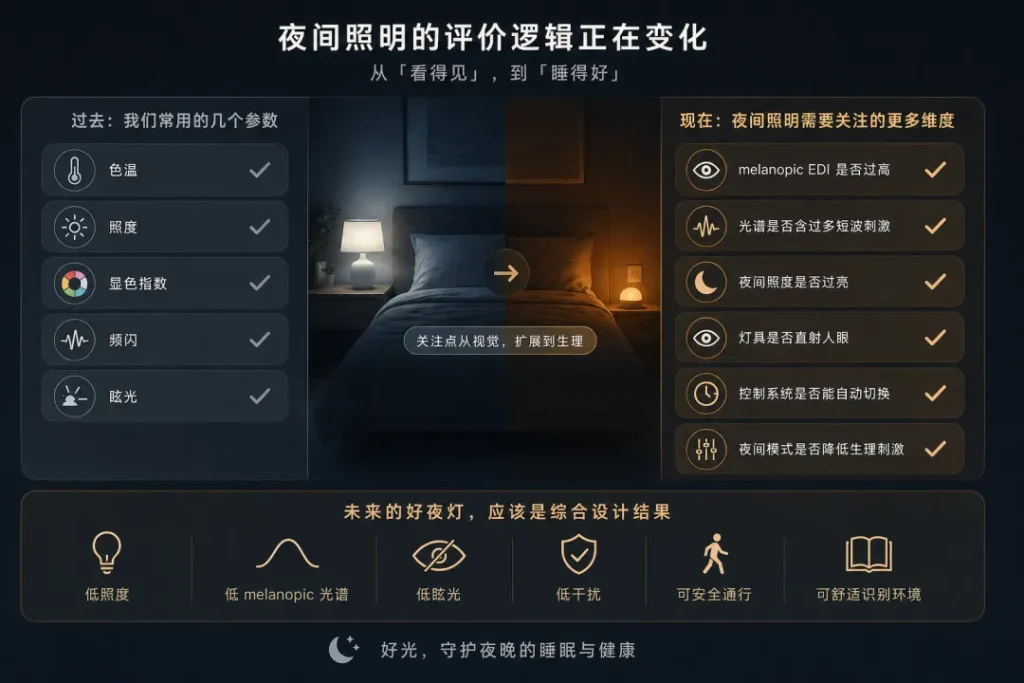
A good circadian nighttime lighting solution is not simply lowering color temperature or dimming the lights, but controlling the light actually received at the user's eyes. The design should use the eye-direction melanopic EDI as the core evaluation metric for nighttime circadian stimulation, while also considering visual illuminance, spectrum, light distribution direction, glare, timing, and usage scenarios.
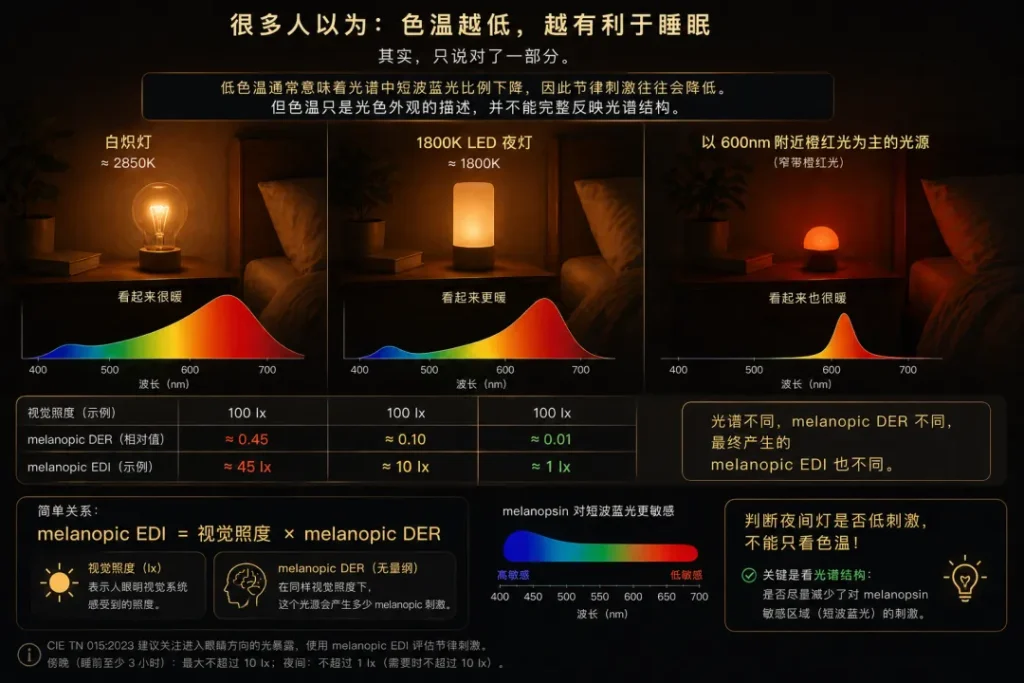
I. Core Evaluation Metrics for Circadian Lighting
melanopic EDI = eye-direction visual illuminance × melanopic DER
- melanopic EDI:Measures the equivalent stimulation of light on the melanopsin system, in units of lx.
- melanopic DER:The relative effectiveness of a spectrum on melanopsin at the same visual illuminance.
- Measurement direction:The evaluation position should be close to the user's eyes and measured along the primary line of sight; do not measure only desktop or floor horizontal illuminance.
- Color temperature boundary:Color temperature only describes the appearance of light color and cannot alone prove that nighttime circadian stimulation is low.
- Metric boundary:CS can serve as a research or product comparison metric, but it belongs to a different evaluation system and should not be mixed with CIE melanopic EDI.

II. Design Goals for Nighttime Light Exposure
According to the nighttime light exposure recommendations in CIE TN 015:2023, the system goals can be divided into the following phases:
| Phase | Time or State | Ocular-direction melanopic EDI Target | Design Focus |
|---|---|---|---|
| Daytime | Daytime activity | Aim for higher daytime light exposure | Daylight first, supporting alertness and stable circadian rhythm |
| Pre-sleep mode | At least 3 hours before planned sleep | ≤ 10 lx | Gradually reduce circadian stimulation while maintaining basic activity and recognition ability |
| Nighttime bathroom-visit mode | Short-term nighttime passage, care, and other necessary activities | As low as possible, and ≤ 10 lx | Low-position, low-illuminance, indirect lighting, avoiding direct glare into the eyes |
| Sleep mode | After falling asleep | Environmental target ≤ 1 lx | Keep as dark as possible, retaining only guide lighting required for safety |
The above values are intended as design control targets, not equivalent to medical efficacy promises, and cannot replace conventional evaluations such as glare, flicker, photobiological safety, and passage safety.

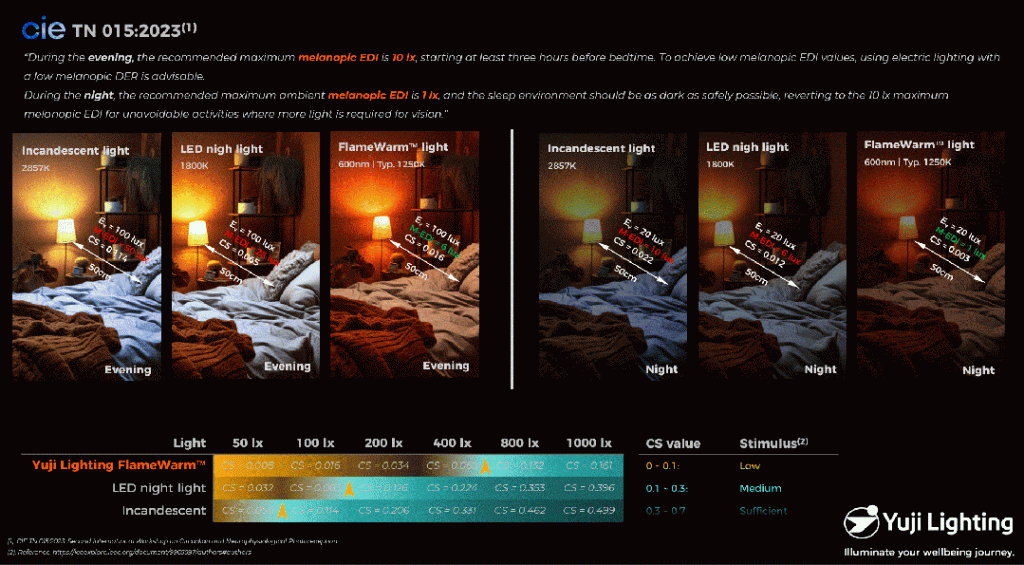
III. Three-level design of nighttime lighting
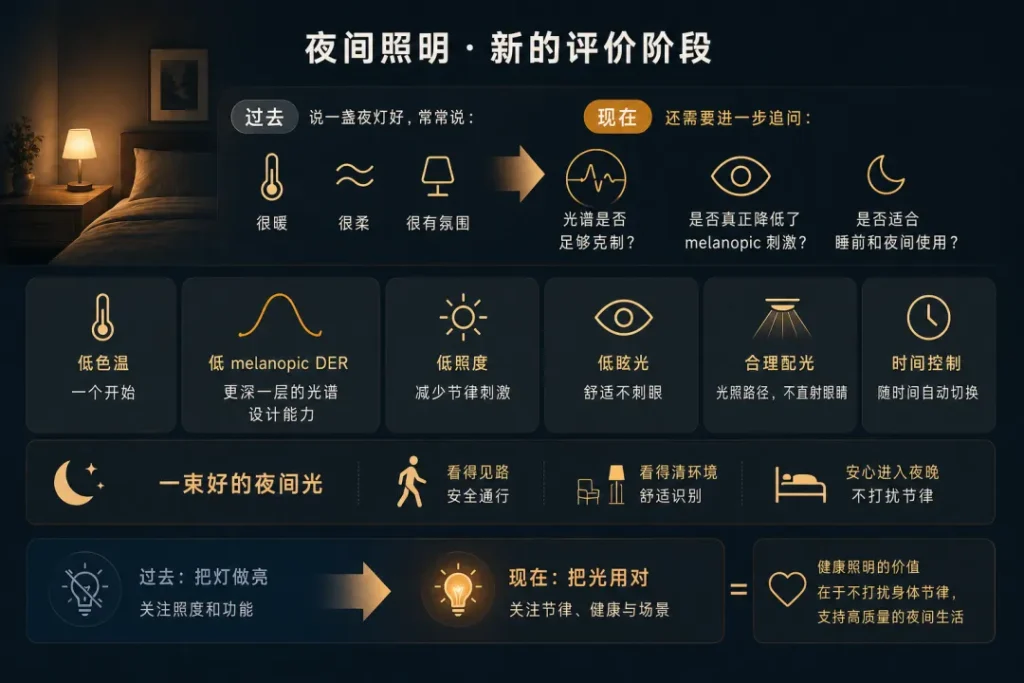
1. Pre-sleep environment
Design target:Begin reducing physiological stimulation approximately 3 hours before bedtime, without making the space dim and difficult to use.
- Use a low melanopic DER spectrum rather than only requiring low color temperature.
- Use bedside indirect light, wall-reflected light, and localized reading light.
- Reduce illuminance toward the eyes and avoid large-area high-brightness luminous surfaces.
- Use narrow-beam task lighting for reading lamps to prevent light from entering the eyes directly.
- Switch gradually over time to avoid abrupt changes in brightness and light color.
Recommended targets:Melanopic EDI toward the eyes ≤ 10 lx; use a low melanopic DER spectrum and indirect, side-rear, or low-position light distribution.

2. Nighttime toilet visits
Design objectives:Allow people to see the path while reducing alerting stimulation and glare.
- Use baseboard lights, under-bed lights, wall-base lights, or low-position guide lights.
- Light should be directed toward the floor and path, not directly into the eyes.
- Use motion sensors or bedside triggers to activate only localized, short-duration lighting.
- Set fade-in and delayed fade-out to avoid sudden bright light.
- In hotel, elderly care, and hospital scenarios, manual forced-on capability should be retained.
Recommended targets:Melanopic EDI in the eye direction should be as close to 1 lx as possible, with a maximum not exceeding 10 lx.
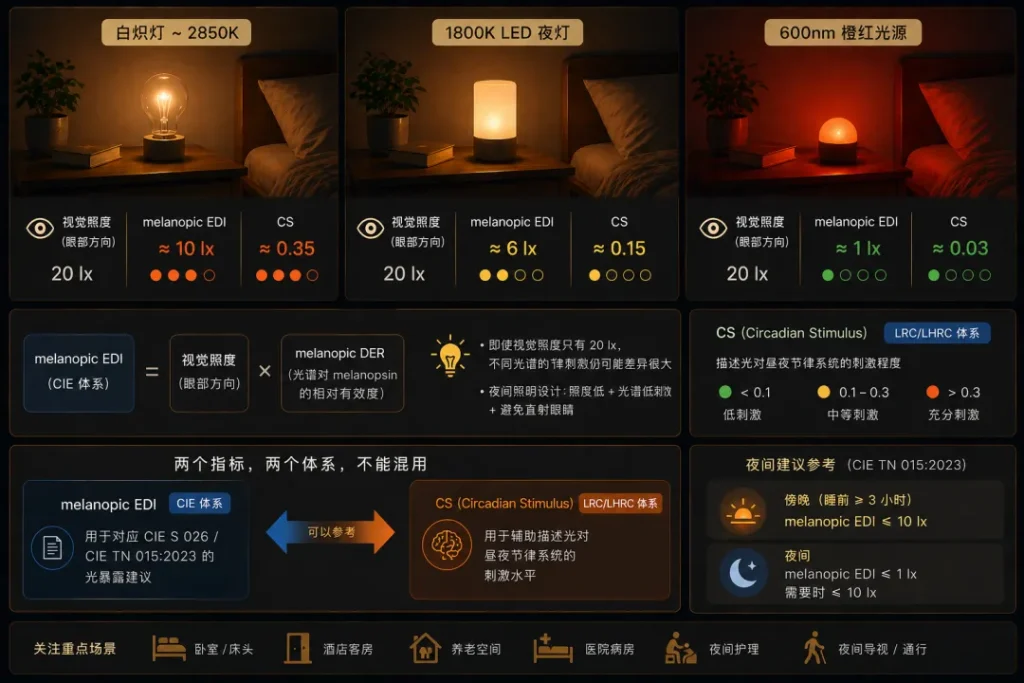
3. Sleep environment
Design objectives:Keep as dark as possible within the allowable safety range.
- Turn off non-essential decorative lights, device indicator lights, and bright display screens.
- Indicator lights that must be retained should use light shielding, dimming, or out-of-sight placement.
- Block outdoor light, light through door gaps, and light leakage from corridors.
- In care scenarios, use localized, directional, short-duration lighting.
Recommended targets:Ambient melanopic EDI ≤ 1 lx, retaining only necessary low-level wayfinding light.
IV. Product system architecture
1. Light source layer
It is recommended to develop three types of light source modules:
- Pre-sleep ambient light module:Adopts a low melanopic DER spectrum, supports continuous dimming, suitable for bedside, wall or ceiling indirect lighting.
- Night-time wayfinding light module:Low-position installation, asymmetric light distribution, strict light shielding, focusing on illuminating the floor and obstacle outlines.
- Essential task light module:Used for caregiving, finding objects and emergency activities, prioritizing local lighting, and automatically returning to a low-stimulation mode after the operation ends.
Light source development should not only specify CCT, but also provide spectral power distribution SPD, melanopic DER, melanopic EDI at different dimming levels, as well as color rendering, flicker, glare and photobiological safety data.

2. Perception and control layer
- Time schedule:Switch according to sunset, daily routine or hotel occupancy mode.
- Human presence or occupancy sensing:Controls the night-time pathway lights.
- Ambient light sensing:Avoid redundant supplemental lighting when existing ambient light is already bright.
- Door sensor or bedside trigger:Determine the nighttime path and necessary lighting areas.
- Manual override:Ensure use by the elderly, patients, caregivers, and in emergency situations.
- Fault strategy:After power recovery, must not default to a high-brightness nighttime state.
3. Recommended control logic
- Daytime:Provide sufficient daytime light exposure.
- Entering the pre-sleep period:Ambient light gradually transitions to low melanopic DER and low eye-level illuminance, ensuring eye-direction melanopic EDI ≤ 10 lx.
- Nighttime getting-up detected:Enable only low-level path lights, fade in gradually and avoid direct eye exposure, and fade out with delay after no occupancy.
- Entering sleep state:Turn off non-essential lighting; ambient melanopic EDI ≤ 1 lx.
- Nursing or emergency operations:Briefly enable essential task lighting; automatically return to night mode after the operation ends.
V. Implementation recommendations for different scenarios
| Scenario | Recommended luminaire combination | Key control points |
|---|---|---|
| Home bedroom | Bedside indirect light + under-bed path light + blackout control | Pre-sleep gradual dimming, automatic sensing for nighttime trips |
| Hotel guest room | Room scene lighting + bedside or bathroom path light | Ready to use upon check-in, clear buttons, one-touch activation of night mode |
| Elderly care space | Soft ambient light + continuous path light + nursing task light | Fall prevention priority, low glare, manual override |
| Hospital wards | Patient ambient light + nurse local task light + bathroom wayfinding light | Nursing procedures do not disturb other patients |
| Nighttime corridors | Low-level continuous wayfinding light + zone-based sensor lights | Maintain path recognition and limit light spill into rooms |
VI. Prototype Verification and Acceptance
For each scenario and dimming level, at minimum the following should be tested:
- Conventional light color metrics such as light source SPD, CCT and color rendering index.
- Vertical illuminance in the direction of the eyes, melanopic EDI and melanopic DER.
- Results under different installation distances, angles and usage postures.
- Flicker, glare and photobiological safety.
- Obstacle recognition and passage safety along the nighttime route.
Measurement positions shall not be limited to the floor or desktop; they shall cover eye-level positions when a person is lying down, sitting on the edge of the bed, standing and walking, as well as the operating positions of caregivers and the most unfavorable direct viewing angles of luminaires.
| Acceptance items | Bedtime mode | Night-time toilet mode | Sleep mode |
|---|---|---|---|
| Melanopic EDI in the eye direction | ≤ 10 lx | As close as possible to 1 lx, and ≤ 10 lx | ≤ 1 lx |
| Path recognition | Compliant | Must be compliant | Not required |
| Direct glare from luminaires | Low | Extremely low | Invisible or extremely low |
| Automatic switching | Required | Required | Required |
| Manual override | Supported | Supported | Supported |
VII. Product Development Implementation Roadmap

Phase 1: Requirements and spectral definition
- Define target scenarios, user groups, and typical installation conditions.
- Establish three sets of target parameters for bedtime, nighttime waking, and sleep.
- Screen low melanopic DER light source solutions and build an SPD database.
Phase 2: Prototype and simulation
- Develop prototypes for bedside lights, path lights, and controllers.
- Complete light distribution simulations for typical rooms.
- Verify melanopic EDI at eye level, not just horizontal illuminance.
Phase 3: Real-world testing
- Set up a real bedroom or hospital room environment.
- Test different distances, angles, wall reflectances, and dimming levels.
- Conduct tests on passage safety, glare perception, and control logic.
Phase 4: Productization
- Finalize parameter packages and control strategies for different scenarios.
- Output spectral, light distribution, installation, and acceptance data.
- Describe product capabilities with verifiable data, and avoid unproven efficacy claims such as "sleep aid" or "treatment."
VIII. Recommendations for External Communication
A good night light should let people safely see their surroundings while reducing unnecessary circadian stimulation at night.
Key messages to convey:
- Nighttime lighting is not just about low color temperature, but about low melanopic stimulation.
- Lamps that look equally dim or warm may differ significantly in physiological stimulation.
- Good nighttime lighting is jointly determined by spectrum, illuminance, direction, scene, and control.
- Product value should be supported by measured data in the eye direction and scene testing.
Avoid directly claiming:
- A single wavelength or color temperature alone can aid sleep.
- melanopic EDI or CS can directly predict individual sleep outcomes.
- Meeting recommended values is equivalent to product certification or medical efficacy certification.